
Why Meridian Logic Matters More Than Memorising Acupuncture Points
Sep 19, 2026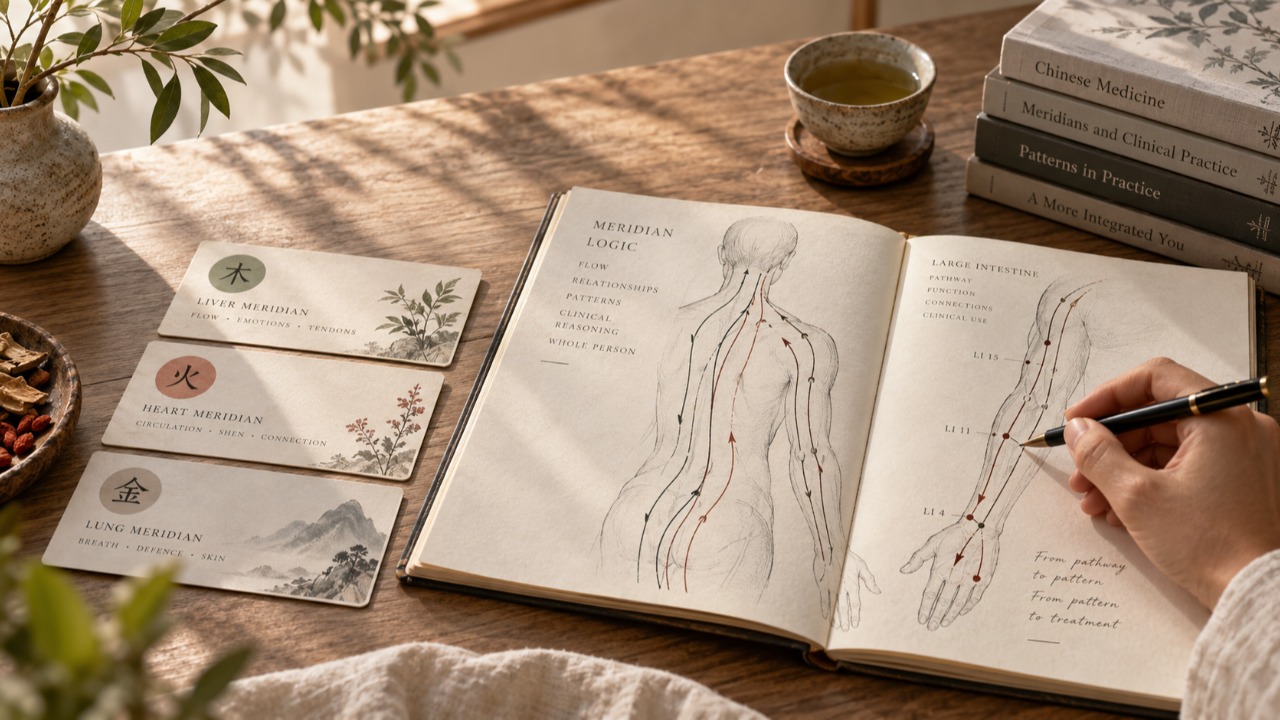
You're treating a patient with lateral elbow pain. You needle the local points — LI 10, LI 11, maybe TE 5. The session is fine. The pain reduces a little. They come back next week. You do it again.
You're getting results. But you're also quietly aware that you don't fully understand why what you're doing works — or why it sometimes doesn't.
That gap is where meridian logic lives. And closing it changes everything about how you practice.
The Memorisation Problem
Most practitioners are taught acupuncture through point locations and protocols. Learn where the points are. Learn which conditions they're indicated for. Combine them in a recipe and needle.
This approach has its place early in training — you need to know where the points are before you can do anything with them. But it has a ceiling. And most practitioners hit it.
The ceiling shows up in a specific way: you can locate points accurately, but you can't fully explain why a given point belongs in a treatment, what it's actually doing relative to the patient's pattern, or why this session landed and last week's session didn't.
Dry needle practitioners often encounter this first. They get good results with local work — then realise they don't have a framework to explain why distal points work, or when to use them. Acupuncturists face a different version of the same problem. The training covered everything in theory. The clinic is a different story. Twelve meridians, dozens of points, pattern after pattern — and not enough time to make it feel automatic.
In both cases, the gap is the same. The technique is there. The underlying framework — the meridian logic that explains what you're doing and why — isn't fully in place yet.
The Meridian Gives the Point Context
A point is not just a location. It's a position on a channel with a pathway, a functional character, and a relationship to a specific organ system.
When you understand the pathway, the point makes sense in a way that memorisation alone can't give you.
Take the Large Intestine channel. It runs from the tip of the index finger up the radial aspect of the arm, through the elbow (LI 10, LI 11), across the shoulder and neck, to finish at the side of the nose. That pathway explains why a practitioner treating lateral elbow pain should be asking about the patient's digestion, bowel function, and the quality of tissue at the nose and face. These aren't separate clinical concerns — they're on the same channel.
It also explains why distal points work. LI 4, in the web of the thumb, is far from the elbow — but it's on the same channel, and it's one of the most effective points for moving stagnation along the entire Large Intestine pathway. If you understand the channel, the distal point isn't counterintuitive. It's obvious.
One of TJ's students described the shift this way: the meridians had always been "random lines" in their mind. After working with the pathway at the level of actual anatomical tissue — feeling the channel, tracing it through the gross muscle-tendon structures they were already needling — they became something else entirely. The anatomy made sense. The points had a reason for being where they were.
Point Categories Create Predictable Logic
Once you understand that each meridian is a system with a pathway and a functional character, point categories become one of the most useful clinical tools you have.
Not all points on a channel do the same thing. Point categories describe the type of action a point tends to have — and knowing these turns point selection from guesswork into something much more deliberate.
A practical example from clinical practice: the three-pronged approach of local, distal, and empirical points.
- Local points act on the tissue and region directly beneath the needle — useful for clearing stagnation and addressing the immediate site of pathology.
- Distal points act along the same channel, often from a considerable distance, moving Qi and Blood through the entire pathway. Their effect is often stronger than local points for releasing stubborn stagnation.
- Empirical points have accumulated clinical evidence for specific indications through centuries of recorded use — they work reliably for particular conditions regardless of channel logic.
A treatment that uses all three is working the problem from three different angles simultaneously. That's a rationale, not a recipe.
The same thinking applies to other point categories — He-Sea points, which draw excess inward and treat the organ directly; Yuan-Source points, which access constitutional Qi; Luo-connecting points, which link coupled channels. Each category has a predictable action. Learning them is not more memorisation — it's learning a grammar. Once you have the grammar, you can construct clinical sentences rather than reciting memorised phrases.
Pattern and Point Choice Belong Together
Meridian logic doesn't operate in isolation from pattern diagnosis — they're two dimensions of the same clinical thinking.
The pattern tells you what is happening at the functional level: deficiency or excess, heat or cold, which organ system, which substances are involved. The meridian and point selection tells you where and how to intervene to address that pattern.
Consider a patient presenting with lower back pain that isn't responding to local treatment. The local work — needling the tender points in the lumbar region — is addressing the site. But if the underlying pattern is Kidney Yang deficiency, the channel most relevant to the constitutional root of that presentation is the Bladder channel (which runs through the entire back) and the Kidney channel itself. Treating locally without addressing the channel and its pattern is treating the branch and leaving the root untouched.
This is exactly what the email one practitioner wrote to TJ described: "The Bladder channel explained why the lower back wasn't responding to local treatment." Once the channel was understood — its pathway, its relationship to Kidney, its role in storing and distributing Jing — the clinical picture clicked into place. The problem wasn't technique. It was context.
An Example of Reasoning Rather Than Recipe-Following
The carpal tunnel presentation is a useful example of what it looks like to reason from the channel rather than from a point recipe.
Most practitioners will go straight to PC7, the textbook carpal tunnel point — and it has genuine clinical logic, sitting directly over the carpal tunnel through which the Pericardium channel and the median nerve both travel.
But understanding the channel means asking: where else along this pathway could there be an entrapment or restriction that's contributing to the presentation? The Pericardium channel runs from the chest, through the pectoral region, down the center of the biceps, medial to the biceps tendon, through the forearm, through the carpal tunnel, to the palm and middle finger.
Any of those locations — the pectoral, the elbow, the wrist — could be a site of restriction that's loading the carpal tunnel from above. Treating PC3 at the elbow, needling at the clavicular margin, addressing the cervical spine: these aren't additions to the recipe. They're expressions of understanding the channel as a continuous anatomical structure.
The result is a treatment that's working with the whole pathway — not just the end-point of a complaint.
Why This Makes Practice More Flexible
Recipe-based practice is brittle. It works when the presentation matches the recipe. When it doesn't — when the patient is complex, when the response to treatment is unexpected, when the textbook protocol isn't landing — a practitioner working from memorisation has nowhere to go.
A practitioner working from meridian understanding has a framework for responding. They can look at what's happening, trace it back to the channel and pattern logic, and adapt. They can change the angle of approach — adding a distal point, changing the depth or direction, shifting to the coupled channel — because they understand why each of those moves would be justified.
The practitioners who get the most out of this work are already getting decent results, but they're also aware they're working harder than they need to. The underlying framework isn't fully in place, so every new presentation requires more thinking. When the framework is in place, clinical decisions come faster. Not because you're looking up the answer — because you can see it.
The Same Learning Move
Understanding meridians structurally and understanding organ patterns structurally are, at their core, the same learning move.
In both cases, you're shifting from isolated memorisation toward seeing relationships — between points and pathways, between signs and patterns, between the physical and the functional.
That's the move that turns Chinese medicine from a library of disconnected facts into a coherent clinical system. And it's available to anyone willing to approach it from that level of understanding rather than from a protocol list.
Next Step: TCM Study Cards
If you're working on building the diagnostic side of this — the organ pattern relationships that underpin good point selection — the free TCM Study Cards are designed to help you see those relationships at a glance.
They're a visual reference for the common organ patterns and their characteristic signs: the kind of material that's most useful when you're building recognition rather than retrieving memorised facts.
👉 https://www.bhaktiatsu.com/TCM-Study-Cards
Stay connected with news and updates!
Join our mailing list to receive the latest news and updates from our team.
Don't worry, your information will not be shared.
We hate SPAM. We will never sell your information, for any reason.
